Indications:
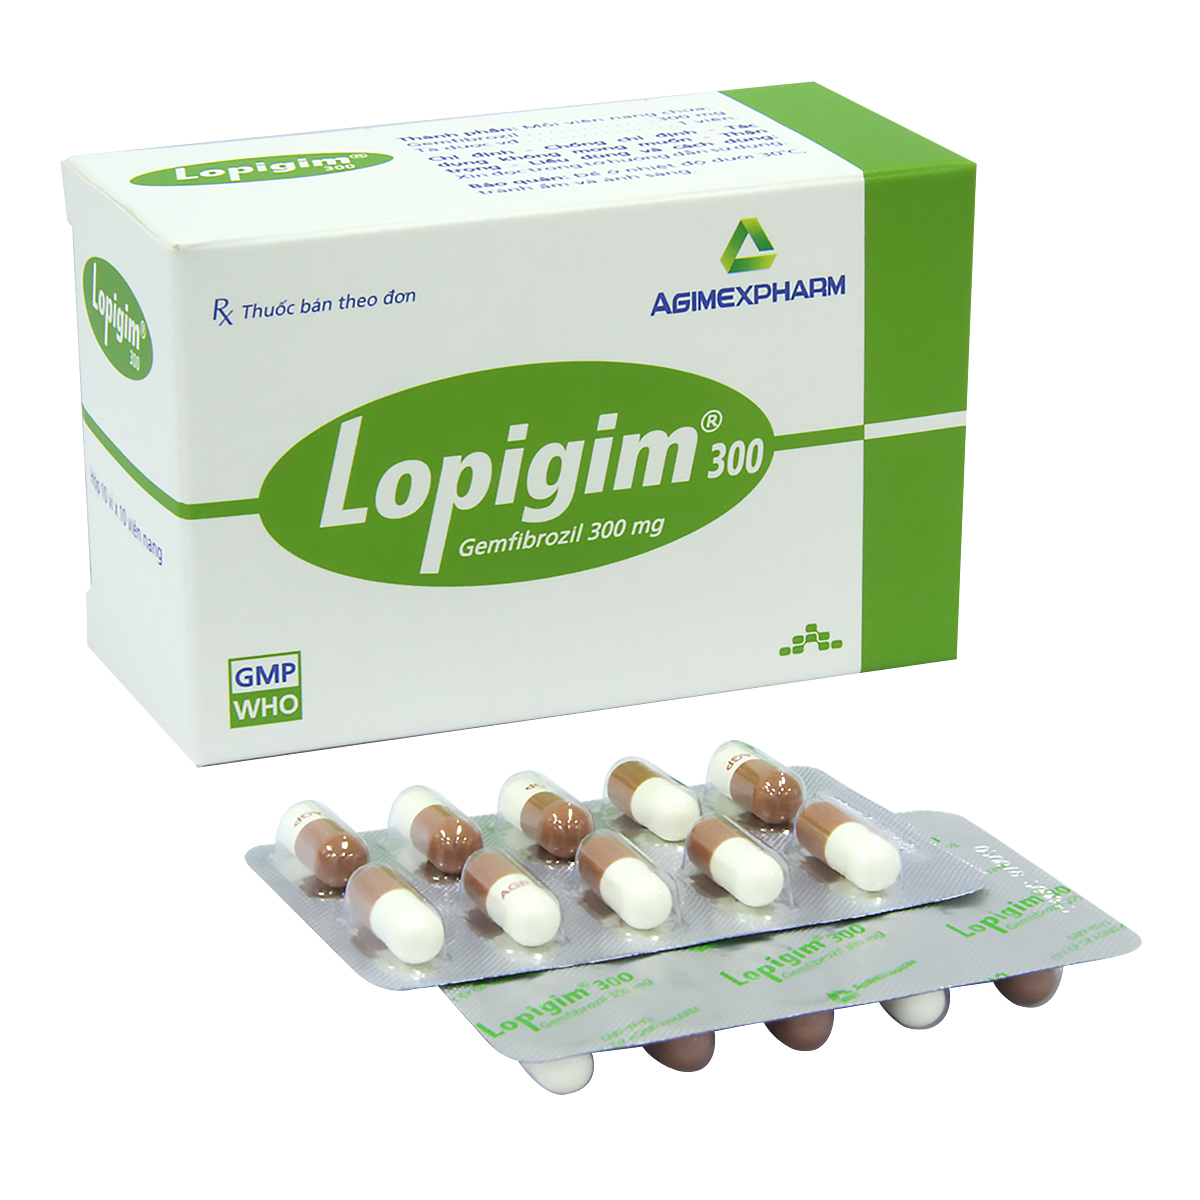
Gemfibrozil is a selective drug for treatment homozygous apoE2/apoE2 hyperlipidemia (type III hyperlipoproteinemia); moderate to severe hypertriglyceridaemia with risk of pancreatitis; familial combined hyperlipidemia accompanied by high VLDL levels; if there is high LDL level, additive low-dose of HMG CoA reductase inhibitors is administered.
Gemfibrozil is indicated for the treatment of hyperlipidemia and reducing the risk of coronary heart disease in type IIb hyperlipidemia patients without history of or symptoms of existing coronary artery disease, who have had an inadequate response to weight loss, dietary therapy, exercise, and other drugs alone and who have the following triad of lipid abnormalities: Low HDL-cholesterol levels in addition to elevated LDL-cholesterol and elevated triglycerides.
Gemfibrozil is indicated for the treatment of patients with severe primary hyperlipidemia (types IV and V hyperlipidemia) and risk of coronary heart disease, abdominal pain typical of pancreatitis, who have had an inadequate response to the diet or other measures alone. Gemfibrozil has no effect on type I hyperlipidemia.
Dosage and administration:
Administration: Oral route.
Dosage:
Prior to initiating gemfibrozil, other medical problems such as hypothyroidism and diabetes mellitus must be controlled as best as possible and patients should be placed on a standard lipid-lowering diet, which should be continued during treatment.
Adults:
The dose range is 900 mg to 1200 mg daily.
The 1,200 mg dose is taken as 600 mg twice daily, half an hour before breakfast and half an hour before the evening meal.
The 900 mg dose is taken as a single dose half an hour before the evening meal.
Elderly (over 65 years old):
As for adults.
Children and adolescents:
Gemfibrozil therapy has not been investigated in children. Due to the lack of data, the use of Lopigim in children is not recommended.
Renal impairment:
In patients with mild to moderate renal impairment (glomerular filtration rate 50 – 80 and 30 – 50 ml/min/1.73 m2, respectively), start treatment at 900 mg daily and assess renal function before increasing dose. Gemfibrozil should not be used in patients with severely impaired renal function.
Hepatic impairment:
Gemfibrozil is contraindicated in hepatic impairment.
Some special attention on the handling of the medicine before and after use:
There are no special requirements for handling this medicine after use.
Contraindications:
Gemfibrozil is contraindicated in cases of:
Hypersensitivity to the active substance or to any of the excipients of the drug.
Hepatic dysfunction including primary biliary cirrhosis.
Severe renal impairment.
History of/or pre-existing gallbladder or biliary tract disease, including gallstones.
Patients with previous history of photoallergy or phototoxic reaction during treatment with fibrates.
Pregnant women and breastfeeding mothers.
Type I hyperlipoproteinemia.
Concomitant use of simvastatin, repaglinide, dasabuvir.
Warnings and precautions for use:
Initial therapy: Laboratory studies should be done to ascertain that the lipid levels are consistently abnormal. Before instituting gemfibrozil therapy, every attempt should be made to control serum lipids with appropriate diet, exercise, weight loss in obese patients, and control of any medical problems such as diabetes mellitus and hypothyroidism that are contributing to the lipid abnormalities.
During treatment: Periodic determination of serum lipids should be obtained, and the drug withdrawn if lipid response is inadequate after three months of therapy. When gemfibrozil is discontinued, an appropriate diet to reduce serum lipid and monitoring of serum lipid should be maintained until the patient’s condition is stabilized, because serum triglyceride and cholesterol levels may increase to baseline.
Muscle disorders (myopathy/ rhabdomyolysis):
There have been reports of myositis, myopathy and markedly elevated creatine phosphokinase associated with gemfibrozil. Rhabdomyolysis has also been reported rarely.
Muscle damage must be considered in any patient presenting with diffuse myalgia, muscle tenderness and/or marked increase in muscle CPK levels (>5x ULN); under these conditions treatment must be discontinued.
Concomitant HMG-CoA reductase inhibitors:
The concomitant administration of gemfibrozil with simvastatin is contraindicated. There have been reports of severe myositis with markedly elevated creatine kinase (CK) and myoglobinuria (rhabdomyolysis) when gemfibrozil and HMG-CoA reductase inhibitors were used concomitantly. Pharmacokinetic interactions may also be present and dosage adjustments may be necessary.
The benefit of further alterations in lipid levels by the combined use of gemfibrozil and HMG-CoA reductase inhibitors should be carefully weighed against the potential risks of such combinations and clinical monitoring is recommended.
A creatine phosphokinase (CPK) level should be measured before starting such a combination in patients with pre-disposing factors for rhabdomyolysis as follows:
- Renal impairment
- Hypothyroidism
- Alcohol abuse
- Age > 70 years
- Personal or family history of hereditary muscular disorders
- Previous history of muscular toxicity with another fibrate or HMG-CoA reductase inhibitor.
In most subjects who have had an unsatisfactory lipid response to either drug alone, the possible benefits of combined therapy with HMG-CoA reductase inhibitors and gemfibrozil does not outweigh the risks of severe myopathy, rhabdomyolysis and acute renal failure.
Use in patients with gallstone formation:
Gemfibrozil may increase cholesterol excretion into the bile raising the potential for gallstone formation. Cases of cholelithiasis have been reported with gemfibrozil therapy. If cholelithiasis is suspected, gallbladder studies are indicated. Gemfibrozil therapy should be discontinued if gallstones are found.
Monitoring serum lipids:
Periodic determinations of serum lipids are necessary during treatment with gemfibrozil. Sometimes a paradoxical increase of (total and LDL) cholesterol can occur in patients with hypertriglyceridemia. If the response is insufficient after 3 months of therapy at recommended doses, treatment should be discontinued and alternative treatment methods considered.
Monitoring liver function:
Elevated levels of ALAT, ASAT, alkaline phosphatase, LDH, CK and bilirubin have been reported. These are usually reversible when gemfibrozil is discontinued. Therefore liver function tests should be performed periodically. Gemfibrozil therapy should be terminated if abnormalities persist.
Monitoring blood counts:
Periodic blood count determinations are recommended during the first 12 months of gemfibrozil administration. Anaemia, leucopenia, thrombocytopenia, eosinophilia and bone marrow hypoplasia have been reported rarely.
Interactions with other medicinal products:
Concomitant use with CYP2C8, CYP2C9, CYP2C19, CYP1A2, UGTA1, UGTA3 and OATP1B1 substrates.
The interaction profile of gemfibrozil is complex resulting in increased exposure of many medicinal products if administered concomitantly with gemfibrozil.
Gemfibrozil potently inhibits CYP2C8, CYP2C9, CYP2C19, CYP1A2, and UDP glucuronyltransferase (UGTA1 and UGTA3) enzymes and also inhibits organic anion-transporting polypeptide 1B1 (OATP1B1). In addition, gemfibrozil is metabolised to gemfibrozil 1-O-β-glucuronide which also inhibits CYP2C8 and OATP1B1.
Concomitant use with hypoglycaemic agents:
There have been reports of hypoglycaemic reactions after concomitant use with gemfibrozil and hypoglycaemic agents (oral agents and insulin). Monitoring of glucose levels is recommended.
Concomitant anticoagulants:
Gemfibrozil may potentiate the effects of coumarin type vitamin K antagonist anticoagulants such as warfarin, acenocoumarol, or phenprocoumon. The concomitant administration of gemfibrozil with these anticoagulants necessitates careful monitoring of prothrombin time (INR – International Normalised Ratio). Caution should be exercised when such a coumarin type vitamin K antagonist anticoagulant is given concomitantly with gemfibrozil. The dosage of the anticoagulant may need to be reduced to maintain desired prothrombin time levels.
Others:
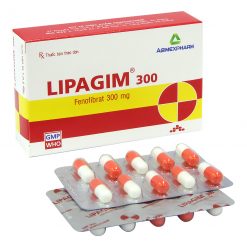
Lopigim 300 capsules contain lactose. Patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take this medication.
Pregnancy and lactation:
Pregnancy:
Gemfibrozil crosses the placenta. There are no adequate and well-controlled studies in pregnant women; gemfibrozil should not be used during pregnancy.
Women who are likely to become pregnant or are using contraceptives should consult their doctor carefully before starting treatment with this medication.
Limited information is available on the fetus toxicity.
Lactation:
It is not known whether gemfibrozil is distributed into human milk. Because gemfibrozil has the potential to cause serious side effects in breast-fed infants, breastfeeding while using this drug is not recommended.
Effects on ability to drive and use machines:
No evidence on the effects of gemfibrozil on the ability to drive and use machines have been performed. However, it should be noted that side effects of the drug such as dizziness, drowsiness may occur.
Interactions, incompatibilities of medicine:
Interaction with other medicinal products and other forms of interaction:
Anticoagulants, coumarin derivatives or indanedione:
Coadministration with gemfibrozil may significantly increase the anticoagulant effect of these medicines; anticoagulant dose should be adjusted based on routine investigation of prothrombin time.
Chenodesoxycholic acid or ursodesoxycholic acid:
The effect of these agents may be reduced when concomitantly used with gemfibrozil, which tends to increase biliary cholesterol saturation.
Lovastatin:
The risk of rhabdomyolysis is increased in concomitant therapy with gemfibrozil: Significant increase in creatine kinase level and myoglobinuria result in acute renal failure which may occur as early as three weeks after initiation of combined therapy or after several months. There is no assurance that periodic monitoring of creatine kinase will prevent the occurrence of severe myopathy or kidney damage.
The interaction profile of gemfibrozil is complex. In vivo studies indicate that gemfibrozil and its metabolite gemfibrozil 1-O-β-glucuronide are potent inhibitors of CYP2C8 (an important enzyme for the metabolism of dabrafenib, loperamide, montelukast, repaglinide, rosiglitazone, pioglitazone, dasabuvir and paclitaxel). Co-administration of gemfibrozil and repaglinide or dasabuvir is contraindicated. In addition, dosing reduction of drugs that are mainly metabolised by CYP2C8 enzyme may be required when gemfibrozil is used concomitantly. In vitro studies have shown that gemfibrozil is a strong inhibitor of CYP2C9 (an enzyme involved in the metabolism of warfarin and glimepiride), but also of CYP2C19, CYP1A2, OATP1B1 and UGTA1 and UGTA3. Gemfibrozil 1-O-β-glucuronide also inhibits OATP1B1.
Repaglinide:
In healthy volunteers, co-administration with gemfibrozil increased the AUC and Cmax of repaglinide by 8.1 fold and 2.4 fold, respectively. In the same study, co-administration with gemfibrozil and itraconazole increased the AUC and Cmax of repaglinide by 19.4 fold and 2.8 fold, respectively. In addition, co-administration with gemfibrozil or with gemfibrozil and itraconazole prolonged its hypoglycaemic effects. Therefore, co-administration of gemfibrozil and repaglinide increases the risk for severe hypoglycaemia and is contraindicated.
Dasabuvir:
Co-administration of gemfibrozil with dasabuvir increased dasabuvir AUC and Cmax (ratios: 11.3 and 2.01, respectively) due to CYP2C8 inhibition. Increased dasabuvir exposure may increase the risk of QT prolongation, therefore, co-administration of gemfibrozil with dasabuvir is contraindicated.
Rosiglitazone:
The combination of gemfibrozil with rosiglitazone should be approached with caution. Co-administration with rosiglitazone has resulted in 2.3-fold increase in rosiglitazone systemic exposure, probably by inhibition of the CYP2C8 isozyme.
HMG-CoA reductase inhibitors:
The concomitant administration of gemfibrozil with simvastatin is contraindicated. The combined use of gemfibrozil and a statin should generally be avoided. The use of fibrates alone is occasionally associated with myopathy. An increased risk of muscle related adverse events, including rhabdomyolysis, has been reported when fibrates are co-administered with statins.
Gemfibrozil has also been reported to influence the pharmacokinetics of simvastatin, lovastatin, pravastatin and rosuvastatin. Gemfibrozil caused an almost 3-fold increased in AUC of simvastatin acid possibly due to inhibition of glucoronidation via UGTA1 and UGTA3, and a 3-fold increase in pravastatin AUC which may be due to interference with transport proteins. One study indicated that the co-administration of a single rosuvastatin dose of 80 mg to healthy volunteers on gemfibrozil (600 mg twice daily) resulted in a 2.2-fold increase in mean Cmax and a 1.9-fold increase in mean AUC of rosuvastatin.
Anticoagulants:
Gemfibrozil may potentiate the effects of coumarin type vitamin K antagonist anticoagulants such as warfarin, acenocoumarol, or phenprocoumon. The concomitant administration of gemfibrozil with these anticoagulants necessitates careful monitoring of prothrombin time (INR).
Bexarotene:
Concomitant administration of gemfibrozil with bexarotene is not recommended. A population analysis of plasma bexarotene concentrations in patients with cutaneous T-cell lymphoma (CTCL) indicated that concomitant administration of gemfibrozil resulted in substantial increases in plasma concentrations of bexarotene.
Bile acid – binding resins:
Reduced bioavailability of gemfibrozil may result when given simultaneously with resin-granule drugs such as colestipol. Administration of the products two hours or more apart is recommended.
Colchicine:
Risk of myopathy and rhabdomyolysis may be increased with concomitant administration of colchicine and gemfibrozil. This risk may be increased in the elderly and in patients with hepatic or renal dysfunction. Clinical and biological monitoring are recommended, especially at the start of combined treatment.
Gemfibrozil is highly bound to plasma proteins and there is potential for displacement interactions with other drugs.
Incompatibilities:
Because there are no studies about the incompatibility of the medicine, it should not be mixed with other medicines.
Undesirable effects:
Most commonly reported adverse reactions are of gastrointestinal character and are seen in approximately 7% of the patients. These adverse reactions do not usually lead to discontinuation of the treatment.
Adverse reactions are ranked according to frequency: Very common (ADR > 1/10), Common (1/100 ≤ ADR < 1/10), Uncommon (1/1,000 ≤ ADR < 1/100), Rare (1/10,000 ≤ ADR < 1/1,000), Very rare (ADR < 1/10,000), can not be estimated from the available data “Frequency not known”.
| System Organ Class | Undesirable effect |
| Blood and lymphatic system disorders | |
| Rare | Bone marrow failure, severe anaemia, thrombocytopenia, leukopenia, eosinophilia |
| Psychiatric disorders | |
| Rare | Depression, decreased libido |
| Nervous system disorders | |
| Common | Vertigo, headache |
| Rare | Neuropathy peripheral, paraesthesia, dizziness, somnolence |
| Eye disorders | |
| Rare | Vision blurred |
| Cardiac disorders | |
| Uncommon | Atrial fibrillation |
| Respiratory, thoracic and mediastinal disorders | |
| Rare | Laryngeal oedema |
| Gastrointestinal disorders | |
| Very common | Dyspepsia |
| Common | Diarrhoea, vomiting, nausea, constipation, abdominal pain, flatulence |
| Rare | Pancreatitis, appendicitis |
| Hepatobiliary disorders | |
| Rare | Jaundice cholestatic, hepatitis, cholelithiasis, cholecystitis, hepatic function abnormal |
| Skin and subcutaneous tissue disorders | |
| Common | Eczema, rash |
| Rare | Angioedema, dermatitis exfoliative, urticaria, dermatitis, alopecia, photosensitivity reaction, pruritus |
| Musculoskeletal and connective tissue disorders | |
| Rare | Rhabdomyolysis, myopathy, myositis, muscular weakness, synovitis, myalgia, arthralgia, pain in extremity |
| Reproductive system and breast disorder | |
| Rare | Erectile dysfunction |
| General disorders | |
| Common | Fatigue |
| Investigations | |
| Rare | Haemoglobin decreased, haematocrit decreased, white blood cell count decreased, blood creatine phosphokinase increased |
Guidelines for ADR management:
In case of severe gastrointestinal ADRs, discontinuance of the drug is required. Patients receiving gemfibrozil and complaining of muscle pain, tenderness, or weakness should have prompt medical evaluation for myositis, including serum creatine-kinase level determination. If myositis is suspected or diagnosed, gemfibrozil therapy should be withdrawn.
Proper diagnostic tests should be performed if there is occurrence of signs suspected to be associated with the hepatobiliary system. Liver function tests and complete blood cell counts should be performed 3 – 6 months after starting gemfibrozil therapy and then every year. Gemfibrozil should be discontinued and not used again if the results of liver function tests increase steadily or excessively, or there are significant abnormalities; generally, the results of abnormal tests are recovered. Gemfibrozil therapy should be discontinued if gallstones are found.
Overdose, management:
Overdose:
Symptoms of overdosage include abdominal pain, diarrhea, nausea, vomiting.
Management:
Treatment of gemfibrozil overdose is symptomatic and supportive. In case of acute gemfibrozil overdose, the stomach should be emptied immediately by induction of emesis or gastric lavage.
Monitoring should be exercised actively for timely measures.
Pharmacodynamics:
Pharmacotherapeutic group: Serum-lipid lowering agent
ATC code: C10AB04.
Gemfibrozil is a non-halogenated fibric acid derivative with hypolipidemic effects. Gemfibrozil reduces triglyceride–rich lipoprotein levels, such as VLDL (very low–density lipoprotein), modestly raise HDL levels (high density lipoprotein) and has variable effects on LDL levels (low density lipoprotein). The effects on VLDL levels probably result primarily from an increase in lipoprotein lipase activity, especially in muscle. This would lead to increased hydrolysis of VLDL triglyceride content and enhanced VLDL catabolism. Gemfibrozil modifies the VLDL component due to decreasing hepatic production of apoC-III, an inhibitor of lipoprotein lipase activity, and also reduces the synthesis of VLDL triglyceride in the liver.
Addition to its lipid-lowering effect, gemfibrozil also decreases platelet aggregation, thus reduces the risk of cardiovascular disease.
The clinical effects of gemfibrozil or any other fibric acid derivatives on lipoprotein levels depend on the starting lipoprotein profile, the presence or absence of hyperlipoproteinemia. Patients with homozygous apoE2/apoE2 hyperlipidemia best responds to gemfibrozil therapy. Elevated triglyceride and cholesterol levels may be dramatically lowered, and tuboeruptive and palmar xanthomas may regress completely. Gemfibrozil also has good effects on angina and intermittent claudication.
Gemfibrozil therapy in patients with mild hypertriglyceridaemia (e.g. triglycerides < 400 mg/dl) or 4.5 mmol/l, usually produces a decrease in triglyceride levels by 50% or more, and increase in HDL cholesterol levels by 15% to 25%, especially in patients with familial combined hyperlipidaemia. Gemfibrozil is effective in patients with severe hypertriglyceridaemia and accompanied by chylomicronemia syndrome. Whereas starting therapy is to reduce maximally fat from the diet as possible, gemfibrozil can both increase lipoprotein lipase activity and decrease triglyceride synthesis in the liver. In these patients, maintenance therapy with gemfibrozil may keep triglyceride concentrations at levels of less than 600 to 800 mg/dl (6.8-9 mmol/l) to prevent complications of pancreatitis and tuboeruptive xanthomas.
Pharmacokinetics:
Absorption:
Gemfibrozil is well absorbed from the gastrointestinal tract after oral administration with a bioavailability close to 100%. As the presence of food alters the bioavailability slightly gemfibrozil should be taken 30 minutes before a meal. Peak plasma levels occur in one to two hours. After administration of 600 mg twice daily a Cmax in the range 15 to 25 mg/ml is obtained.
Distribution
The drug is extensively distributed and the concentrations in liver, kidney and intestine are higher than that in plasma. Volume of distribution is 0.14 ± 0.03 l/kg. The plasma protein binding of gemfibrozil and its main metabolite are at least 97%.
Biotransformation
Gemfibrozil undergoes oxidation of a ring methyl group to form successively a hydroxymethyl and a carboxyl metabolite (the main metabolite). This metabolite has a low activity compared to the mother compound gemfibrozil and an elimination half-life of approximately 20 hours. Glucuronidation to gemfibrozil 1-O-β-glucuronide is another important elimination pathway for gemfibrozil in man.
The enzymes involved in the metabolism of gemfibrozil are not known. The interaction profile of gemfibrozil and its metabolites is complex. In vitro and in vivo studies have shown that gemfibrozil inhibits CYP2C8, CYP2C9, CYP2C19, CYP1A2, UGTA1, UGTA3 and OATP1B1. Gemfibrozil 1-O-β-glucuronide also inhibits CYP2C8 and OATP1B1.
Elimination
Gemfibrozil is eliminated mainly by metabolism. Approximately 70% of the administered human dose is excreted in the urine, mainly as conjugates of gemfibrozil and its metabolites. Less than 6% of the dose is excreted unchanged in the urine. Six percent of the dose is found in faeces. The total clearance of gemfibrozil is in the range 100 to 160 ml/min, and the elimination half-life is in the range 1.3 to 1.5 hours. The pharmacokinetics is linear within the therapeutic dose range.
In patients with renal failure, the excretion of gemfibrozil is reduced but in a lesser extent than other fibrates. The clearance of gemfibrozil is 1.7 ± 0.4 ml/minute/kg. No pharmacokinetic studies have been performed in patients with impaired hepatic function.
Storage conditions, shelf – life, quality specification of the medicine:
Storage conditions: Store the medicine below 300C. Protect from humidity and light.
Shelf – life: 36 months from the manufacture date.
Quality specification: In house specification