Indications:
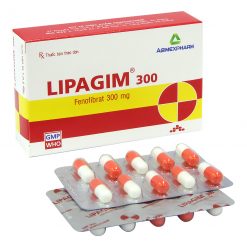
LIPAGIM 50 is indicated as an adjunct to diet in the treatment of:
- Elevated LDL-C, total cholesterol, triglycerides and Apo B, and to increase HDL-C in adult patients with primary hypercholesterolemia or mixed dyslipidemia.
- Severe hypertriglyceridemia in adult patients.
Administration, dosage:
Administration:
The capsules should be orally swallowed whole during a meal.
The initial pre-treatment diet should be continued. Response to treatment should be monitored by determining serum lipid levels. Treatment should be discontinued if adequate response is not achieved after 2 months at the maximum recommended dose of 3 capsules/day. Consideration should be given to reducing the dosage of fenofibrate if lipid levels fall significantly below the targeted range.
Dosage:
Primary hypercholesterolemia or mixed dyslipidemia: 3 capsules/time/day.
Severe hypertriglyceridemia:
Recommended dose is 1 – 3 capsules/day. Dosage should be individualized according to patient response and should be adjusted if necessary following repeat lipid determinations at 4 to 8 week intervals.
The maximum dose is 3 capsules/time/day.
Renal impairment patients:
Treatment with fenofibrate capsules should be initiated at a dose of 1 capsule/day in patients having mild to moderately impaired renal function and increased only after evaluation of the effects on renal function and lipid levels at this dose. The use of fenofibrate capsules should be avoided in patients with severe renal impairment.
Elderly patients:
Dose selection for the elderly should be made on the basis of renal function.
Some special attention on the handling of the medicine before and after use:
There are no special requirements for handling this medicine after use.
Contraindications:
Hypersensitivity to fenofibrate, fenofibric acid or any of the excipients of drug.
Patients with severe renal impairment including those receiving dialysis.
Patients with active liver disease including those with primary biliary cirrhosis and unexplained persistent liver function abnormalities (see Warnings and precautions for use).
Nursing mothers.
Patients with preexisting gallbladder disease (see Warnings and precautions for use).
Warnings and precautions for use:
Conditions requiring caution:
Secondary causes of hyperlipidemia:
Before considering treatment with fenofibrate, secondary causes of hypercholesterolemia, such as uncontrolled type 2 diabetes, hypothyroidism, nephrotic syndrome, dysproteinemia, hepatic cholestasis or alcoholism, should be addressed proper manner.
Secondary causes of hypercholesterolemia following drug therapy may be encountered when taking diuretics, beta-blockers, estrogens, progestins, estrogen-progestin oral contraceptives, immunosuppressive agents or protease inhibitors. In these cases, it is necessary to ascertain whether the hyperlipidemia is primary or secondary in nature (possible increase in lipid levels caused by the administration of these drugs).
Liver function:
As with other lipid-lowering agents, an elevation of transaminases has been observed during treatment with fenofibrate in some patients. In the majority of cases, these elevations were transient, minor and asymptomatic. It is recommended check transaminase levels every 3 months during the first 12 months of treatment and then periodically. Particular attention will be given to patients developing an increase in transaminase levels and treatment must be interrupted in the event of an increase in aspartate aminotransferase (ASAT) and alanine aminotransferase (ALAT) levels above 3 times the upper limit of normal. When symptoms indicative of hepatitis appearance (e.g. jaundice, pruritus) and this diagnosis has been confirmed by laboratory tests, treatment with fenofibrate should be stopped.
Pancreas:
Pancreatitis has been reported in patients receiving fenofibrate, this could be linked to a lack of effectiveness in patients with severe hypertriglyceridemia, or to a direct effect of the drug, or to a phenomenon secondary to the formation of lithiasis or biliary sludge obstructing the common bile duct.
Muscle:
Muscle toxicity, including very rare cases of rhabdomyolysis, with or without renal damage has been reported during the administration of fibrates or other lipid-lowering agents. The incidence of these disorders increases in cases of hypoalbuminemia and pre-existing renal insufficiency.
Patients at risk of myopathy or rhabdomyolysis, including those aged over 70, or with a personal or family history of hereditary muscle damage, or impaired renal function, or hypothyroidism, or with high consumption of alcohol, are exposed to a higher risk of rhabdomyolysis. For these patients, the benefit-risk balance of treatment with fenofibrate must be carefully evaluated.
Muscle toxicity should be suspected in patients presenting with diffuse myalgia, myositis, muscle cramps and weakness and/or significant elevations of CPK (> 5 times the upper limit of normal). In these cases, treatment with fenofibrate should be stopped.
The risk of muscle toxicity may be increased if the drug is administered with another fibrate or inhibitor HMG-CoA reductase, particularly in cases of pre-existing muscle disease. Therefore, co-prescription of fenofibrate with an HMG-CoA reductase inhibitor or another fibrate should be reserved for patients with severe combined dyslipidemia and high cardiovascular risk without a history of muscle disease, and under close monitoring signs of muscle toxicity. The combination with rosuvastatin at a dose of 40 mg is contraindicated (see section Contraindications and Interactions).
Renal function:
Fenofibrate is contraindicated in patients with severe renal impairment (see Contraindications).
Fenofibrate should be used with caution in patients with mild to moderate renal impairment. The dosage should be adjusted in patients with an estimated glomerular filtration rate between 30 and 59 ml/min/1.73 m² (see Dosage).
Reversible increases in serum creatinine levels have been reported in patients receiving fenofibrate as monotherapy or in combination with statins. Increases in serum creatinine were generally stable over time, with no evidence of continued increases in levels during long-term treatment and tended to return to baseline levels after treatment was stopped.
During clinical studies, 10% of patients had an increase in creatinine greater than 30 µmol/l compared to its initial value during concomitant administration of fenofibrate and simvastatin versus 4.4% of patients receiving a statin as monotherapy. 0.3% of patients receiving the combination had a clinically relevant increase in creatinine to values > 200 µmol/l.
Treatment should be stopped when the creatinine level is above 50% of the upper limit of normal. It is recommended to measure creatinine levels during the first 3 months after initiating treatment and periodically thereafter.
Pregnancy and lactation:
Pregnancy:
No data are available on the use of fenofibrate in pregnant women.
The results of studies carried out in animals have not revealed any teratogenic effects. However, embryotoxic effects were observed at doses corresponding to those of maternal toxicity. The potential risk to humans therefore remains unknown.
Therefore, Lipagim 50 should only be used during pregnancy after careful assessment of the benefit and risk ratio.
Lactation:
There are no data on the excretion of fenofibrate and/or its metabolites into breast milk. A risk to the newborns/infants cannot be excluded. Therefore, fenofibrate should not be used during breast-feeding.
Effects on ability to drive, use machines:
Fenofibrate has no or negligible influence on the ability to drive and use machines.
Interactions, incompatibilities of medicine:
Interaction of the drug with other drugs and other types of interactions:
Rosuvastatin 40 mg: Risk of additional adverse effects (dose-dependent) such as rhabdomyolysis. This association is contraindicated.
HMG-CoA reductase inhibitors and other fibrates: The risk of serious muscle toxicity is increased if fenofibrate is used in combination with HMG-CoA reductase inhibitors or other fibrates. This combination should be used with caution, under close monitoring for signs of muscle toxicity.
Ezetimibe: Risk of cholelithiasis due to increased biliary excretion of cholesterol.
Oral anticoagulants: Fenofibrate increases the effects of oral anticoagulants and may increase the risk of bleeding. However, if this combination is required, it is recommended to reduce the dosage of anticoagulants by a third at the start of treatment and if necessary to gradually readjust the dose according to the INR (International Normalized Ratio).
Cyclosporine: Severe but reversible cases of impairment of renal function have been reported following concomitant administration of fenofibrate and cyclosporine. In these patients, renal function should be carefully monitored and treatment with fenofibrate stopped in the event of significant changes in test parameters.
Glitazones: Cases of paradoxical and reversible reduction of HDL-cholesterol have been reported with concomitant administration of fenofibrate and glitazones. However, it is recommended to monitor HDL-cholesterol levels if these two medications are associated, and to stop one of the two treatments if the HDL-cholesterol level is too low.
Cytochrome P450 enzymes: In vitro human liver microsome studies show that fenofibrate and fenofibric acid are not inhibitors of the CYP3A4, CYP2D6, CYP2E1 or CYP1A2 isoforms of cytochrome (CYP) P450; on the other hand, they are weak inhibitors of CYP2C19 and CYP2A6 and weak to moderate inhibitors of CYP2C9, at therapeutic concentrations.
Patients co-administered with fenofibrate and drugs with a narrow therapeutic window metabolized by CYP2C19, CYP2A6 and especially CYP2C9 should be carefully monitored and, if necessary, dosage adjustment of these drugs is recommended.
Colchicine: Cases of myopathy, including rhabdomyolysis, have been reported when fenofibrate was used concomitantly with colchicine, caution should be exercised when prescribing fenofibrate with colchicine.
Incompatibilities:
Because there are no studies of drug incompatibility, do not mix this drug with other drugs.
Undesirable effects:
Side effects are classified according to frequency: Very common (ADR ≥ 1/10), common (1/100 ≤ ADR < 1/10), uncommon (1/1,000 ≤ ADR < 1/100), rare (1/10,000 ≤ ADR < 1/1,000), very rare (ADR < 1/10,000); can not be estimated from the available data “Not known”.
The most commonly reported ADRs during fenofibrate therapy are digestive, gastric or intestinal disorders.
Blood and lymphatic system disorders:
Rare: Haemoglobin and leukocytes decreased.
Immune system disorders:
Rare: Hypersensitivity.
Nervous system disorders:
Uncommon: Headache.
Vascular disorders:
Uncommon: Thromboembolism (pulmonary embolism, deep vein thrombosis).
Respiratory, thoracic and mediastinal disorders:
Not known: Interstitial lung disease.
Gastrointestinal disorders:
Common: Gastrointestinal signs and symptoms (abdominal pain, nausea, vomiting, diarrhea, flatulence).
Uncommon: Pancreatitis.
Hepatobiliary disorders:
Common: Transaminases increased.
Uncommon: Cholelithiasis.
Rare: Hepatitis.
Not known: Jaundice, complications of cholelithiasis (cholecystitis, cholangitis, biliary colic).
Skin and subcutaneous tissue disorders:
Uncommon: Cutaneous hypersensitivity (e.g. rash, pruritus, urticaria).
Rare: Alopecia, photosensitivity reactions.
Not known: Severe skin reactions (e.g. erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis).
Musculoskeletal, connective tissue disorders:
Uncommon: Muscle disorders (e.g. diffuse myalgia, myositis, cramps and muscle weakness).
Not known: Rhabdomyolysis.
Reproductive system and breast disorders:
Uncommon: Sexual dysfunction.
General disorders:
Not known: Fatigue.
Investigations:
Common: Blood homocysteine level increased.
Uncommon: Blood creatinine increased.
Rare: Blood urea increased.
Guidance on handling ADR: Medicine is discontinued.
Inform your doctor or pharmacist if any of the side effects occurs while using the medicine.
Overdose and management:
Overdose:
Only anecdotal cases of fenofibrate overdosage have been reported. In the majority of cases no overdose symptoms were reported.
Management:
No specific antidote is known. If an overdose is suspected, symptomatic treatment and appropriate measures. Fenofibrate is not hemodialysable.
Pharmacodynamics:
Pharmacotherapeutic group: Serum lipid reducing agents/cholesterol and triglyceride reducers/fibrates.
ATC code: C10AB05.
Fenofibrate is a fibric acid derivative whose lipid modifying effects reported in humans are mediated via activation of peroxisome proliferator activated receptor type α (PPARα). Through activation of PPARα, fenofibrate increases lipolysis and elimination of atherogenic triglyceride-rich particles from plasma by activating lipoprotein lipase and reducing production of apoprotein C-III. Activation of PPARα also induces an increase in the synthesis of apoproteins A-I and A-II.
The above stated effects of fenofibrate on lipoproteins lead to a reduction in very low- and low-density fractions (VLDL and LDL) containing apoprotein B and an increase in the high-density lipoprotein fraction (HDL) containing apoprotein AI and AII. In addition, through modulation of the synthesis and the catabolism of VLDL fractions fenofibrate increases the LDL clearance and reduces small dense LDL, the levels of which are elevated in the atherogenic lipoprotein phenotype, a common disorder in patients at risk for coronary heart disease.
During clinical trials with fenofibrate, total cholesterol was reduced by 20 to 25%, triglycerides by 40 to 55% and HDL cholesterol was increased by 10 to 30%. In hypercholesterolaemic patients, where LDL cholesterol levels are reduced by 20 to 35%, the overall effect on cholesterol results in a decrease in the ratios of total cholesterol to HDL cholesterol, LDL cholesterol to HDL cholesterol, or Apo B to Apo AI (all of which are markers of atherogenic risk).
Treatment with fibrates may reduce coronary heart disease events but they have not been shown to decrease all cause mortality in the primary or secondary prevention of cardiovascular disease.
Extravascular deposits of cholesterol (tendinous and tuberous xanthoma) may be markedly reduced or even entirely eliminated during fenofibrate therapy.
Patients with raised levels of fibrinogen treated with fenofibrate have shown significant reductions in this parameter, as have those with raised levels of Lp(a). Other inflammatory markers such as C reactive protein (CRP) are reduced with fenofibrate treatment.
The uricosuric effect of fenofibrate leading to the reduction in uric acid levels of approximately 25% should be of additional benefit in those dyslipidaemic patients with hyperuricaemia.
Fenofibrate has been shown to possess an anti-aggregatory effect on platelets in animals and in a clinical study (thrombocytopenia due to ADP, arachidonic acid and epinephrine).
Children:
Adverse reactions similar to those reported in adults have been reported in children: Leukopenia, abnormal liver function, renal failure, hepatitis, jaundice, myositis, and rhabdomyolysis. Overall, the safety and efficacy of fenofibrate in children and adolescents have not been established.
Pharmacokinetics:
Absorption:
Maximum plasma concentrations (Cmax) occur within 4 to 5 hours after oral administration. Plasma concentrations are stable during continuous treatment in any given individual.
The absorption of fenofibrate is increased when administered with food.
Distribution:
Fenofibric acid is strongly bound to plasma albumin (more than 99%).
Transformation:
After oral administration, fenofibrate is rapidly hydrolysed by esterases to the active metabolite fenofibric acid. No unchanged fenofibrate can be detected in the plasma. Fenofibrate is not a substrate for CYP3A4. No hepatic microsomal metabolism is involved.
Elimination:
Fenofibrate is mainly excreted in the form of fenofibric acid and its glucurono conjugate. Practically all the drug is eliminated within 6 days. In elderly patients, total plasma clearance is not modified.
Kinetic studies following the administration of a single dose and continuous treatment have demonstrated that the drug does not accumulate. Fenofibric acid is not eliminated by haemodialysis.
The plasma elimination half-life of fenofibric acid is approximately 20 hours.
Storage conditions, shelf life, quality specification of the medicine:
Storage conditions: Protect from humidity and light, below 300C.
Shelf life: 36 months from the manufacture date.
Quality specification: In house.